
Herniated Disc MRI Signs: Protrusion, Extrusion, and Red Flags
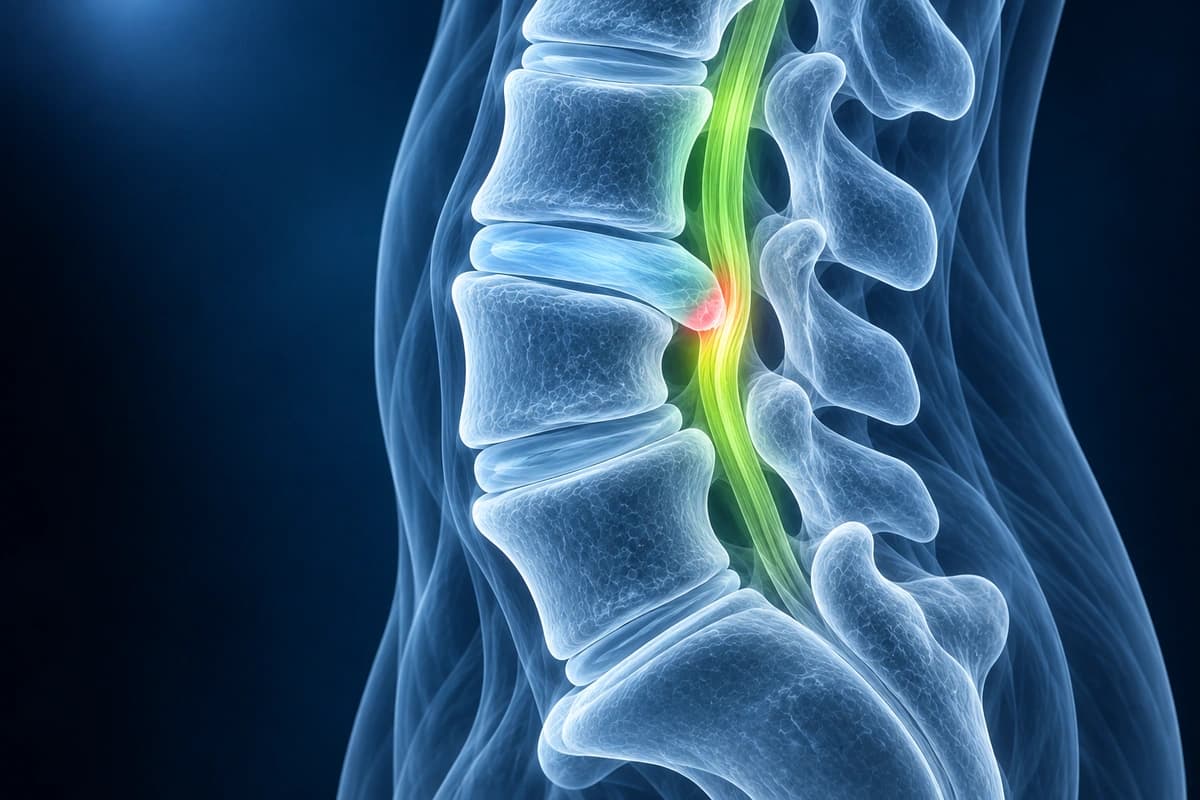
A herniated disc occurs when the nucleus pulposus extrudes through a defect in the annulus fibrosus, potentially compressing adjacent neural structures. Disc herniations are classified by morphology (protrusion, extrusion, sequestration), location (central, paracentral, foraminal, extraforaminal), and level. MRI is the gold standard for evaluating disc herniations and their effect on the spinal cord and nerve roots.
Common Symptoms
- Sharp or burning radicular pain radiating down one arm or leg along a specific dermatomal distribution
- Numbness and tingling in the hand, fingers, foot, or toes corresponding to the compressed nerve root
- Muscle weakness in the myotome supplied by the affected nerve root, such as foot drop with L4–L5 herniation
- Axial neck or low back pain that is often overshadowed by the radicular component
- Pain worsened by Valsalva maneuvers such as coughing, sneezing, or straining
- Positive straight-leg raise (Lasègue's sign) at less than 60° for lumbar herniations affecting L4–S1
What Is a Herniated Disc?
A useful report should distinguish a contained protrusion from an extrusion or sequestration, then connect the level and zone to the affected nerve root. For symptom expectations, see whether a herniated disc can heal on its own, and compare degenerative context in the Pfirrmann disc grading guide.
MRI is usually the best study for disc hydration, annular tears, nerve root contact, and cord signal change. CT can help when the disc is calcified, bone detail matters, or MRI is limited by hardware, but clinical review is still needed to connect the imaging level with the exam. If you are checking your own series before an appointment, open the free spine MRI viewer or read the spine MRI reading guide alongside the condition notes.
Disc Protrusion vs Extrusion: What Your MRI Report Means
A disc protrusion and a disc extrusion are both herniations: disc material pushed past the normal edge of the disc in one limited area. The difference is shape. In a protrusion the part that sticks out is narrower than its base on the disc. In an extrusion the escaped material is wider than its neck, or has broken away completely.
How radiologists word a herniation
- “Broad-based disc protrusion at L4–L5”
- “Left paracentral disc protrusion contacting the traversing S1 nerve root”
- “Disc extrusion with caudal migration”
- “Sequestered disc fragment” or “free fragment”
- “Diffuse disc bulge without herniation”
Bulge, protrusion, extrusion and sequestration
These words come from a shared nomenclature of the North American spine and neuroradiology societies. A bulge is a shallow overhang spread around a large part of the disc edge and is not counted as a herniation. A sequestration is an extrusion in which the fragment has lost all contact with its disc, and migration means the material has moved away from the gap it came through. The terms describe shape and position; they do not say what caused the change or whether it hurts.
Disc protrusions are also common in people without back pain. A review of pain-free adults found them in 29% of 20-year-olds and 43% of 80-year-olds, so the report is read alongside your symptoms and examination.
Does the type change treatment?
A bigger-sounding word is not automatically worse news. In a systematic review of people treated without surgery, herniations shrank on follow-up imaging in 96% of sequestrations, 70% of extrusions, 41% of protrusions and 13% of bulges. Guidelines base the choice between waiting, injections and surgery on symptoms and nerve findings, with MRI used to confirm a level that matches them. New bladder or bowel problems or numbness in the saddle area need same-day care for possible cauda equina syndrome.
Questions to ask about your disc report
- Is it a protrusion, an extrusion or a sequestered fragment, and at which level?
- Which nerve root does it touch, and does that match where my leg or arm hurts?
- Could the herniation shrink on its own, and when would a repeat MRI be useful?
- Which symptoms should send me for urgent care?
What Does a Herniated Disc Look Like on MRI?
- Disc material extending beyond the vertebral body margin
- Protrusion: broad-based disc extension with intact outer annulus
- Extrusion: disc material extending through the annulus with narrow neck
- Sequestration: free disc fragment separated from parent disc
- Nerve root compression or displacement
- Spinal cord compression with or without signal changes (cervical/thoracic)
- Calcified disc material or endplate osteophytes on CT when bone detail changes treatment planning
- Pfirrmann grading of disc degeneration
Frequently Asked Questions
How does MRI grading help characterize a herniated disc?
The Pfirrmann grading scale (I–V) classifies intervertebral disc degeneration on sagittal T2-weighted MRI based on signal intensity, disc height, and homogeneity of the nucleus pulposus. A grade I disc is bright and homogeneous; grade V is completely black with lost disc height. Herniation type is further described as protrusion, extrusion, or sequestration based on the relationship of displaced nucleus to the annular margin. Modic endplate changes (type I edema, type II fatty conversion, type III sclerosis) on the adjacent vertebral bodies indicate active inflammation or chronic degeneration and correlate with axial pain severity.
Which nerve root is compressed and how does that affect symptoms?
Each lumbar and cervical nerve root supplies a predictable dermatomal strip of skin and a myotomal group of muscles. A posterolateral L4–L5 herniation typically compresses the L5 root, causing numbness along the dorsum of the foot and weakness of great-toe extension (extensor hallucis longus). L5–S1 herniation compresses S1, producing lateral foot numbness and reduced ankle plantar flexion with a diminished Achilles reflex. Cervical C6 compression causes lateral forearm and thumb numbness with biceps weakness; C7 produces middle-finger numbness and triceps weakness. Accurate dermatomal mapping guides surgical planning and post-treatment assessment.
What are cauda equina red flags and why do they require emergency care?
Cauda equina syndrome occurs when a massive central disc herniation compresses multiple sacral nerve roots simultaneously. Red flags include bilateral leg weakness, saddle anaesthesia (S3–S5 dermatomal numbness around the perineum and inner thighs), and dysfunction of bladder, bowel, or sexual function — often presenting as urinary retention with overflow incontinence. These findings mandate same-day emergency MRI and surgical decompression, typically within 24–48 hours of onset, to prevent permanent sphincteric and motor deficits. Any delay significantly worsens neurological prognosis.
How is a herniated disc different from facet joint syndrome?
A herniated disc more often produces dermatomal arm or leg pain from nerve root contact, while facet joint syndrome usually causes axial neck or back pain that worsens with extension and rotation. MRI can show both problems in the same spine, so the report should be reviewed with the symptom pattern, neurological exam, and clinician plan rather than treated as a stand-alone diagnosis.
Sources
- Fardon DF, Williams AL, Dohring EJ, Murtagh FR, Gabriel Rothman SL, Sze GK. Lumbar disc nomenclature: version 2.0: recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology and the American Society of Neuroradiology. Spine J. 2014;14(11):2525-2545.
- Pfirrmann CW, Metzdorf A, Zanetti M, et al. Magnetic resonance classification of lumbar intervertebral disc degeneration. Spine (Phila Pa 1976). 2001;26(17):1873-1878.
- Chiu CC, Chuang TY, Chang KH, Wu CH, Lin PW, Hsu WY. The probability of spontaneous regression of lumbar herniated disc: a systematic review. Clin Rehabil. 2015;29(2):184-195.
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR Am J Neuroradiol. 2015;36(4):811-816.
- Jensen TS, Karppinen J, Sorensen JS, et al. Vertebral endplate signal changes (Modic change): a systematic literature review of prevalence and association with non-specific low back pain. Eur Spine J. 2008;17(11):1407-1422.
- Ahn UM, Ahn NU, Buchowski JM, et al. Cauda equina syndrome secondary to lumbar disc herniation: a meta-analysis of surgical outcomes. Spine (Phila Pa 1976). 2000;25(12):1515-1522.
- Kreiner DS, Hwang SW, Easa JE, et al. An evidence-based clinical guideline for the diagnosis and treatment of lumbar disc herniation with radiculopathy. Spine J. 2014;14(1):180-191.
Related Articles
Discover the natural healing process of herniated discs, resorption rates, and when intervention is needed.
Safe and effective exercises for herniated disc recovery, including McKenzie method, core stabilization, and movements to avoid.
Compare CT and MRI scans, their strengths for different conditions, radiation exposure, cost, and when each is the better choice.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer