
CT vs MRI: Which Scan Do You Need?
Compare CT and MRI scans, their strengths for different conditions, radiation exposure, cost, and when each is the better choice.
Key Takeaways
- CT uses ionizing X-rays and excels at bone detail, fractures, and rapid trauma evaluation
- MRI uses magnetic fields (no ionizing radiation) and excels at ligaments, cartilage, discs, nerves, and bone marrow
- For acute trauma and bony fracture characterization, CT is fast and definitive
- For ligament tears, disc herniation, cartilage injury, and most spine and joint problems, MRI is the standard
- CT typically costs less and finishes in minutes; MRI costs more and takes 20–45 minutes
- Pacemakers, certain implants, and severe claustrophobia may shift the choice toward CT even when MRI would otherwise be ideal
What Is the Difference Between CT and MRI?
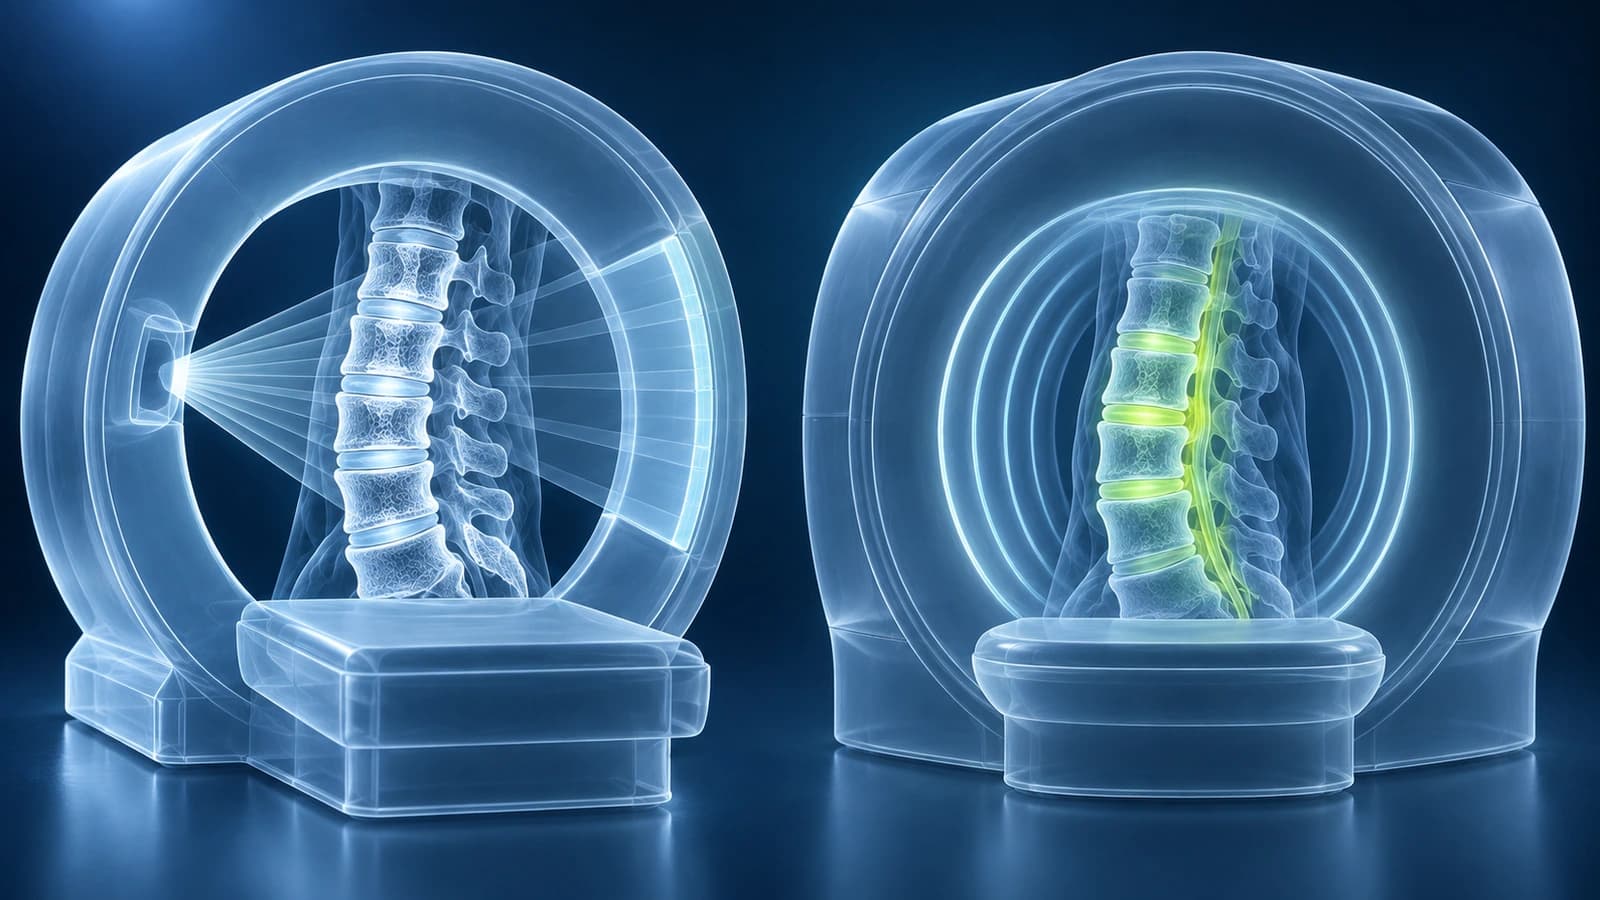
CT builds cross-sectional images from X-rays, so it shows bone in fine detail within minutes but uses ionizing radiation. MRI uses a magnetic field and radio waves, with no radiation, and shows discs, nerves, ligaments, cartilage and bone marrow far better. When back pain with sciatica needs imaging, MRI is usually preferred; for an acute fracture, CT usually comes first.
CT (computed tomography) and MRI (magnetic resonance imaging) are the two most common cross-sectional imaging tests in musculoskeletal medicine. They look superficially similar — both produce slice-by-slice images you can scroll through — but they use completely different physics, expose you to different risks, and excel at imaging different tissues. Choosing the wrong one wastes time, money, and in some cases radiation.
This guide explains how each modality works, what each one shows best, the cost and radiation differences, and how to think about which scan answers your specific clinical question.
How CT Works
A CT scanner rotates an X-ray tube around your body and uses many projections to reconstruct a 3D volume of attenuation values measured in Hounsfield units (HU). Bone is bright (≈+1000 HU), water is zero, fat is negative, and air is very negative (≈−1000 HU). A modern multi-slice CT can image the entire spine or chest in seconds with sub-millimeter resolution. Iodinated contrast can be injected intravenously to highlight blood vessels and inflamed or vascular tissue.
CT's greatest strengths are speed and bone detail. A trauma CT of the cervical spine takes well under a minute, which matters when a patient cannot stay still or is critically injured. Cortical bone, fracture lines, calcifications, and bone fragments in the spinal canal show with extraordinary clarity.
How MRI Works
MRI uses a strong magnetic field (typically 1.5T or 3T) and pulsed radiofrequency energy to excite hydrogen nuclei in water and fat, then measures the signal as those nuclei relax. Different pulse sequences (T1, T2, PD, STIR, fat-saturated, diffusion) highlight different tissues. Unlike CT, MRI does not use ionizing radiation. Gadolinium contrast can be injected intravenously to evaluate inflammation, infection, and tumors.
MRI's greatest strength is soft tissue contrast. Ligaments, tendons, cartilage, menisci, labra, nerves, discs, the spinal cord, muscle, and bone marrow are all visible with much higher contrast resolution than CT. This is why MRI is the standard for imaging the brain, spinal cord, ACL/meniscus, rotator cuff, hip labrum, and any suspected occult fracture in the bone marrow. The trade-off is time (15–45 minutes per study) and motion sensitivity.
When Is CT Better Than MRI?
CT is preferred for acute trauma evaluation, complex fractures (cervical spine, pelvis, calcaneus, acetabulum), surgical planning where 3D bone reconstruction matters, and any patient who cannot tolerate or safely undergo MRI (cardiac pacemakers without MR-conditional certification, certain cochlear implants, retained ferromagnetic foreign bodies near the eye or spine, severe claustrophobia without sedation). CT myelography — CT performed after intrathecal contrast injection — is the alternative for spinal cord and nerve root assessment when MRI is contraindicated.
CT also wins when timing matters: stroke triage, suspected pulmonary embolism, acute abdominal pain, and any patient who cannot lie still for the 20+ minutes an MRI requires. For occult fractures of the scaphoid, hip, or sacrum, CT is more sensitive than radiographs but less sensitive than MRI for marrow edema in the first 48–72 hours.
When Is MRI Better Than CT?
MRI is preferred for nearly every soft tissue question: ligament tears, meniscal injuries, labral tears, rotator cuff disease, tendon pathology, cartilage assessment, disc herniation, spinal stenosis, nerve compression, bone marrow edema, occult fractures, infection, and most musculoskeletal tumors. For the spine, MRI is the standard of care for evaluating disc disease, the cord, the conus, the cauda equina, and infection or tumor in the marrow or epidural space. See our guide on herniated disc for a typical example.
MRI is also the preferred follow-up modality for known soft tissue diagnoses, because it can reproduce the exact same imaging without adding ionizing radiation each time. For pediatric and pregnant patients, MRI is preferred whenever the clinical question can be answered without contrast, because of the absent radiation risk.
Is CT or MRI Safer? Radiation, Cost, and Scan Time
A typical musculoskeletal CT delivers 2–10 mSv (lumbar spine CT roughly 6 mSv, head CT roughly 2 mSv) — equivalent to several months to a few years of average background radiation. MRI delivers zero ionizing radiation. Out-of-pocket cash prices in the U.S. commonly run $300–1,500 for CT and $700–3,000+ for MRI without insurance, with MR arthrography and 3T magnets at the higher end. CT scans usually take under 5 minutes of table time; MRI typically takes 20–45 minutes per body part.
Iodinated CT contrast carries a small risk of allergic reaction and nephrotoxicity in patients with reduced kidney function. Gadolinium MRI contrast carries a different (also small) risk profile, including nephrogenic systemic fibrosis in advanced renal disease and gadolinium retention concerns.
CT or MRI for Back Pain and Sciatica?
Uncomplicated acute low back pain, with or without sciatica, usually does not need imaging. Imaging may be considered after about six weeks without improvement or sooner for red flags. Read our guide to reading a spine MRI.
Frequently Asked Questions
Is MRI always better than CT?
No. MRI has better soft tissue contrast and no radiation, but CT is faster, cheaper, and superior for bone detail and acute trauma. The right choice depends entirely on what tissue you need to image and how quickly you need an answer.
How much radiation does a CT scan deliver?
A musculoskeletal CT typically delivers 2–10 mSv depending on body part and protocol. For comparison, average background radiation is roughly 3 mSv per year. Modern low-dose protocols continue to reduce these doses substantially.
Why is MRI so much slower?
MRI builds an image by exciting hydrogen nuclei with multiple radiofrequency pulses and reading the signal as they relax. Each pulse sequence takes several minutes, and a complete musculoskeletal study uses 4–8 sequences. CT collects all the data in one continuous rotation, which is why it is so much faster.
Can I have an MRI with a pacemaker?
Many modern pacemakers are MR-conditional and can be safely imaged with appropriate precautions and device interrogation. Older pacemakers and some implants remain a contraindication. Always disclose every implant, foreign body, and prior surgery to the MRI technologist before scanning.
What is a CT myelogram and when is it used?
A CT myelogram is a CT scan performed after intrathecal injection of iodinated contrast into the spinal subarachnoid space. It is used when MRI is contraindicated or when MRI artifact (typically from spinal hardware) prevents adequate evaluation of the spinal cord and nerve roots. It is more invasive than MRI but provides high-resolution canal anatomy.
Sources
- Mettler FA Jr, Huda W, Yoshizumi TT, Mahesh M. Effective doses in radiology and diagnostic nuclear medicine: a catalog. Radiology. 2008;248(1):254-263.
- Russo RJ, Costa HS, Silva PD, et al. Assessing the risks associated with MRI in patients with a pacemaker or defibrillator. N Engl J Med. 2017;376(8):755-764.
- Expert Panel on Neurological Imaging; Hutchins TA, Peckham M, Shah LM, et al. ACR Appropriateness Criteria Low Back Pain: 2021 Update. J Am Coll Radiol. 2021;18(11S):S361-S379.
- Expert Panel on Neurological Imaging and Musculoskeletal Imaging; Beckmann NM, West OC, et al. ACR Appropriateness Criteria Suspected Spine Trauma. J Am Coll Radiol. 2019;16(5S):S264-S285.
- Chou R, Qaseem A, Owens DK, Shekelle P. Diagnostic imaging for low back pain: advice for high-value health care from the American College of Physicians. Ann Intern Med. 2011;154(3):181-189.
- RadiologyInfo.org (Radiological Society of North America and American College of Radiology). Radiation Dose from X-Ray and CT Exams.
Related Articles
Decode your spine MRI report, understand disc levels, signal changes, and common findings explained in plain language.
Learn when 3T spine MRI can help for subtle nerve, cord, inflammatory, or post-surgical questions, and when routine 1.5T spine MRI is usually enough.
Related Conditions
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer